
Co-creation in health research: from participation to meaningful influence

Co-creation in health research: from participation to meaningful influence

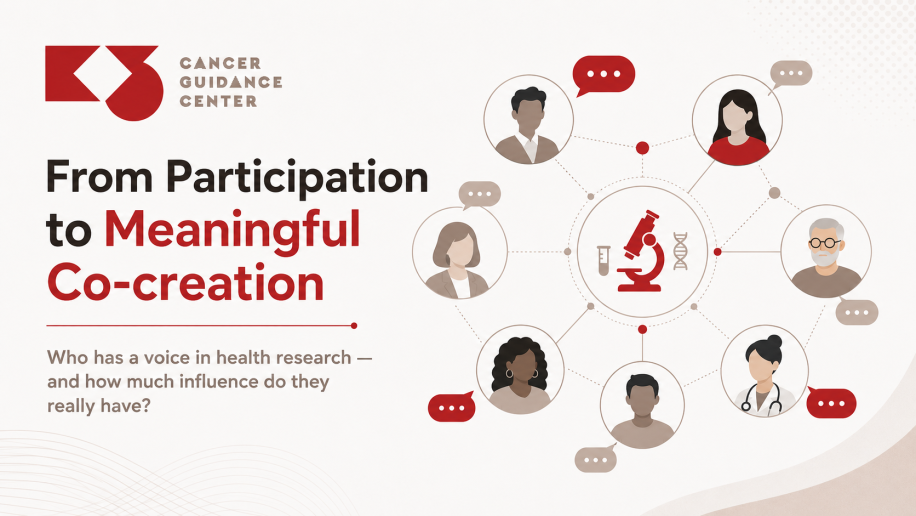
A new scientific study proposes a framework for understanding who participates in research, when they participate, how they contribute — and how much influence they actually have

Co-creation is becoming increasingly important across public health, research, social innovation and the design of healthcare services. Patients, caregivers, citizens, healthcare professionals, researchers and communities are more frequently being invited to contribute to the development of interventions, services and solutions.

Yet an important question remains:

What does “participation” actually mean?

The presence of a patient or community representative in a meeting does not necessarily mean that they can influence the design, decisions or outcomes of a research project. Similarly, being asked to complete a survey is fundamentally different from helping to design an intervention, interpret findings or determine how results are shared.

A new open-access study, published on 19 August 2026 in the Journal of Public Health, addresses this challenge. Katrina Messiha, Mai J. M. Chinapaw, Johannes C. F. Ket, Renée I. Wink and Teatske M. Altenburg developed the Co-creation Roles Framework, an operational framework designed to systematically describe and classify the roles of different stakeholders in co-creation research.

Moving beyond “who was involved?”

One of the study’s most valuable contributions is its shift away from simply recording whether stakeholders participated towards examining the nature, depth and quality of that participation.

The framework captures eight key dimensions:

  • the research stage at which participation occurs,
  • the target group or stakeholder involved,
  • the aim of involvement,
  • how stakeholder knowledge is used,
  • the level of engagement and influence,
  • the form of co-creation,
  • the platform through which engagement takes place,
  • and the duration of engagement.

The relevant question therefore becomes much more precise than “Were patients or citizens involved?”

Instead, researchers can ask:

When were they involved? What were they asked to contribute? How was their knowledge used? And how much influence did they actually have over decisions?

What did the study find?

To demonstrate the practical application of the framework, the researchers conducted a systematic review following PRISMA guidance.

They analysed 39 scientific articles representing 19 youth-focused public health projects based on co-creation, Youth Participatory Action Research or Community-Based Participatory Research approaches.

The analysis revealed substantial variation in the ways stakeholders were engaged.

One particularly striking finding was that, under the strict definition used in the framework, none of the 19 projects reached the highest level of engagement — “empowerment”, where stakeholders hold genuine decision-making authority.

During the implementation stage, consultation and involvement were the most frequent levels of engagement, while consultation was also the most common approach during evaluation.

This finding matters.

It demonstrates that describing a project as “co-created” does not automatically mean that the people for whom an intervention is being developed have meaningful power to shape it.

Participation should not end when the research ends

Another important finding concerned dissemination and reporting.

Only 4 of the 19 projects included a reporting stage extending beyond conventional academic publication.

In some cases, young stakeholders were involved in presenting findings, communicating results within their communities, or developing dissemination materials and practical tools. Overall, however, stakeholder involvement in the final stages of the research process remained limited.

This is highly relevant to health research.

People who contribute their lived experience, time and knowledge to a study should not be considered merely a source of data. They can also play an important role in interpreting findings, shaping key messages and helping return knowledge to the communities from which it originated.

From patient participant to patient co-creator

This discussion has particular relevance for cancer research and cancer care.

Patients and caregivers hold a form of knowledge that clinical evidence alone cannot provide: the lived experience of illness and care.

They understand what treatment means in everyday life; where administrative, social or practical barriers interfere with care; whether a digital health service is genuinely understandable and accessible; which questions remain unanswered; and which outcomes actually matter to the people living with cancer.

Using this knowledge is not simply a matter of representation.

It is a matter of research quality.

For a patient-support organisation such as Kapa3, co-creation therefore means more than inviting patients into an existing process. It requires creating the conditions in which lived experience can become knowledge, knowledge can shape design, and design can ultimately lead to more relevant, accessible and person-centred services.

A framework for planning future research

The authors emphasise that the Co-creation Roles Framework may be valuable not only for describing completed research, but also for planning and evaluating future projects.

Research teams may use it prospectively to clarify stakeholder roles from the beginning, while funders, ethics committees and scientific journals could potentially use such structured approaches to assess how clearly and meaningfully stakeholder participation has been planned and reported.

At the same time, the framework should not yet be regarded as a definitive standard.

The authors explicitly call for external validation across diverse co-creation settings. They also recognise an important limitation: non-academic stakeholders were not directly involved in developing the framework itself, which may limit its sensitivity to some experiential and contextual understandings of stakeholder roles.

Recognising these limitations is itself an important part of advancing more rigorous participatory research.

The next challenge: not simply more participation, but more meaningful participation

Co-creation should not become another box to tick in a research proposal.

The more important challenge is to be able to demonstrate:

who had a voice, when that voice was heard, how it influenced decisions and what ultimately changed because of that contribution.

As healthcare moves towards more participatory, person-centred and digitally supported models of care, the shift from research about patients to research with patients, and ultimately towards research shaped together with patients, may become one of the defining requirements for research that is both scientifically robust and genuinely relevant to people’s lives.

Scientific source

Messiha K, Chinapaw MJM, Ket JCF, Wink RI, Altenburg TM. Development and application of a framework for classifying stakeholder roles in co-creation research: a Health CASCADE study. Journal of Public Health. Published 19 August 2026. DOI: 10.1007/s10389-026-02881-2.

Messiha_et_al-2026-Journal_of_Public_Health

Modern Oncology: When Survival Is Not Enough

New therapies, “hidden” effects and the need to assess not only how long patients live, but how they live

Modern Oncology: When Survival Is Not Enough

New therapies, “hidden” effects and the need to assess not only how long patients live, but how they live

Modern oncology is changing at an unprecedented pace. Immunotherapies, antibody–drug conjugates (ADCs), bispecific antibodies and new targeted therapies are creating treatment opportunities that would have been unimaginable only a few years ago.

Cancer treatment is becoming increasingly personalised and tailored to the biological and molecular characteristics of each tumour, while overall survival is being extended for many people living with cancer.

Yet alongside this remarkable scientific progress, a critical question is emerging:

What does it really mean to live longer after — or with — cancer?

A recent Nature Medicine editorial, entitled “Oncology must confront hidden side effects”, highlights precisely this challenge. While cancer drug development is advancing at remarkable speed, the approaches used to record, assess and manage long-term treatment-related toxicities — and their impact on patients’ quality of life — have not evolved at the same pace.

When a “mild” side effect becomes a major burden

Therapeutic success can create a new reality: people are living longer, but some must also manage treatment-related adverse effects for months, years or even for the rest of their lives.

An adverse event classified clinically as low-grade is not necessarily insignificant to the person experiencing it.

A persistent rash, diarrhoea, stomatitis or other symptoms may substantially affect daily functioning, psychological wellbeing and social life when they continue over long periods.

Similarly, some immune-related adverse events associated with immune checkpoint inhibitors can become chronic, persist for years or even be irreversible.

This highlights an important limitation of the Common Terminology Criteria for Adverse Events (CTCAE), which are widely used to classify and grade treatment-related adverse events.

The duration of adverse events is not adequately reflected, while functional and psychological consequences may also remain outside traditional toxicity assessment.

As a result, what may be considered “manageable” according to conventional clinical criteria can feel very different to the patient living with it every day.

Quality of life cannot be an afterthought

A second important issue is the timing of quality-of-life evidence.

In some cases, quality-of-life findings are reported considerably later than the primary results of a clinical trial, and sometimes after a new drug has already been approved.

This means that patients making treatment decisions during the early years of a new therapy may not yet have a complete picture of how it could affect their daily functioning, emotional wellbeing and overall quality of life.

At the same time, the questionnaires and tools used to assess quality of life need to evolve continuously.

And this cannot happen without the direct involvement of patients themselves.

The experiences and priorities of people receiving treatment should form part of how treatment impact is assessed, rather than being treated as information that is added later.

The example of daraxonrasib

The Nature Medicine editorial highlights the pan-RAS inhibitor daraxonrasib as a telling example. The therapy has shown important survival benefits for patients with aggressive RAS-driven advanced pancreatic cancer, a setting in which treatment options have historically been limited.

At the same time, most patients experienced acneiform rash, with diarrhoea and stomatitis also reported as lower-grade treatment-related adverse events.

Full quality-of-life data — including information on daily functioning and emotional wellbeing — were not yet available because follow-up remained relatively short.

This example illustrates a much wider issue.

If we know that a therapy can significantly extend life, but we do not yet fully understand what that life will be like, an essential part of the information is missing from the conversation between patients and their healthcare teams.

This also has direct implications for informed consent.

Whenever evidence is available, patients need information not only about response rates and survival but also about the potential short- and long-term consequences of treatment for their everyday lives.

The same treatment is not experienced in the same way by everyone

The toxicity profile of a treatment is not identical for every patient.

It may vary according to the drug’s mechanism of action, a person’s physical condition, co-existing long-term conditions, genetic background and other individual characteristics.

Particular attention is needed for populations that have historically been excluded from, or underrepresented in, clinical trials, as their experiences of treatment-related toxicity may differ.

The editorial points, for example, to sex-related differences in adverse events associated with immunotherapy and racial disparities in adverse events observed with CAR-T cell therapy.

This makes real-world data particularly important.

Clinical trials remain fundamental to establishing the safety and efficacy of new treatments. However, broader use in everyday clinical practice may reveal treatment effects that were not fully captured in the populations included in initial studies.

One example is the bispecific antibody amivantamab in lung cancer, where the full extent and severity of some skin toxicities became clearer after a broader patient population was exposed to the treatment.

Moving beyond clinical silos

This changing landscape also demands a different approach to the organisation of cancer care.

The adverse effects of modern cancer therapies do not always fit within a single organ system or medical specialty.

Traditional clinical and disciplinary silos can limit the transfer of knowledge needed to identify, monitor and manage emerging toxicities effectively.

The response therefore needs to be interdisciplinary.

Collaborative networks, updated guidance, systematic reporting, dedicated registries and effective knowledge exchange are increasingly important so that new or rare adverse effects can be recognised early and managed appropriately.

Above all, the patient voice must be heard

Perhaps the most important change concerns how we define treatment success itself.

Survival remains a fundamental goal of oncology.

But it cannot be the only one.

We also need to understand whether people can work, move, sleep, eat, participate in family and social life, maintain as much independence as possible and manage the effects of treatment on their everyday lives.

In other words, we need to know not only how much time a treatment adds to life, but also what that time means to the person living it.

Patients should therefore not enter the process only at the end, as recipients of treatment.

Their perspectives need to be incorporated from the design of clinical trials and assessment tools through to post-approval monitoring and the real-world use of new cancer therapies.

From survival to living after — and with — cancer

Progress in oncology is undeniable, and it brings genuine hope.

The next challenge is to ensure that longer survival is accompanied by quality of life, functioning, meaningful information, participation and dignity.

Modern cancer care therefore needs to move beyond asking only:

“How much longer can this patient live?”

and give equal importance to another question:

“How will this person live during that additional time?”

For Kapa3, this discussion goes to the heart of truly person-centred cancer care: care that sees not only the disease and the treatment, but the person, their everyday life, their needs, their choices and the life that continues during and after cancer.

Source and references

Main source:
Nature Medicine. “Oncology must confront hidden side effects.” Volume 32, July 2026. Published online 8 July 2026. DOI: 10.1038/s41591-026-04554-9.

  1. Barron CC et al. Journal for ImmunoTherapy of Cancer. 2023;11.
  2. Gyawali B et al. Lancet Oncology. 2025;26–e89.
  3. O’Reilly EM et al. New England Journal of Medicine. 2026. DOI: 10.1056/NEJMoa2605555.
  4. Unger JM et al. Journal of Clinical Oncology. 2022;40:1474–1486.
  5. Rayapureddy AK et al. Journal of Clinical Oncology. 2026;44.
  6. Hines MR et al. Transplantation and Cellular Therapy. 2023;29:438.e1–438.e16.

find more s41591-026-04554-9

“Myrto” under Scientific Evaluation: Transparency, Evidence and Human Oversight in Social Navigation for Oncology Patients

“Myrto” under Scientific Evaluation: Transparency, Evidence and Human Oversight in Social Navigation for Oncology Patients

The first closed scientific testing workshop of the Digital Health and Social Rights Navigator has been completed

Athens, 6 July 2026

The first closed scientific testing and evaluation workshop of “Myrto”, the Digital Health and Social Rights Navigator developed by the Cancer Patient Guidance Centre – Kapa3, was successfully completed.

The workshop was organised by the Cancer Patient Guidance Centre – Kapa3, with the support of René Descartes – Cnam College and the participation of SimasiaAI. It functioned as a dynamic scientific co-design workshop, bringing together specialised professionals from the fields of healthcare, social care, information technology and personal data protection.

The process was closed and strictly experimental in nature and did not constitute a public presentation of a completed product. Its purpose was to evaluate the behaviour of the application through hypothetical and fully anonymised scenarios, to record correct responses and areas requiring improvement, and to use expert feedback for the next phase of development.

The project “Myrto – Health and Social Rights Navigator” is being developed as a knowledge-based digital social navigation system, guided by the principles of explainable, transparent and human-centred Artificial Intelligence.

Its aim is to transform complex legal, administrative and social information into clear, evidence-based and practically useful guidance for oncology patients, caregivers and citizens.

“Myrto” does not replace professional social, legal, medical or clinical judgement. It operates as a supportive information and navigation tool, with clearly defined functional boundaries, human oversight and the possibility of referral to the competent services and professionals of Kapa3.

The programme is implemented with the support of the TIMA Charitable Foundation.

From Information to Understandable Knowledge

During the workshop, the need that led to the creation of “Myrto” was presented, along with the real barriers faced by patients and caregivers when seeking information on social rights, benefits and administrative procedures.

Particular emphasis was placed on addressing digital and informational exclusion. “Myrto” is designed to transform fragmented and often difficult-to-understand information into simple, structured and comprehensible guidance.

A Thematically Specialised and Curated Knowledge Base

The project’s technical partner, SimasiaAI, presented the operation of the application and the architecture used for information retrieval and synthesis.

“Myrto” uses a hybrid search mechanism that combines text retrieval and semantic search techniques, with the aim of identifying the information most relevant to the user’s question. The application operates on a thematically specialised and curated knowledge base.

A central element of its design is the traceability of information, namely the ability to link an answer to the source on which it is based. The use of validated sources reduces the risk of unsupported responses and enables the identification, review and correction of issues through a process of continuous maintenance, regular updating and adaptation to evolving guidelines and regulatory requirements.

Explainability and Human-Understandable Answers

The evaluation did not focus only on whether “Myrto” retrieves the correct information, but also on whether it can present that information in a clear, understandable and conceptually coherent way.

This approach strengthens trust, responsible use of the tool and the meaningful empowerment of citizens through a response-generation system that supports a transparent, evidence-based and human-supervised knowledge ecosystem, in which every piece of information is understandable, verifiable and connected to its source.

Data Protection and Compliance by Design

Personal data protection and regulatory compliance are embedded from the design stage of the application, in accordance with the principles of data protection by default and by design.

During the workshop, only hypothetical or fully anonymised cases were used. Particular emphasis was placed on the principles of data minimisation, anonymisation and secure processing. These principles are directly linked to contemporary requirements for the responsible development of Artificial Intelligence systems, the protection of special categories of data and compliance with the European regulatory framework.

Live Testing of Hypothetical Scenarios

The professionals who participated in the workshop tested the application individually and in small groups, using only hypothetical and fully anonymised cases. The testing was based on an approach that evaluated the behaviour of the system, examining not only whether the final answer was correct, but also whether the overall operation of the application was safe, understandable and appropriate for the specific request.

Disability Certification through KEPA

In one of the key scenarios, “Myrto” was asked to guide a hypothetical patient who did not know how to start the disability certification procedure through KEPA. The system retrieved the main steps of the process, organised the information in an understandable format and provided relevant references to the sources.

Participants evaluated:

  • the accuracy of the information,
  • the completeness of the steps,
  • the clarity of the language,
  • and the practical usefulness of the answer.

Travel from the Region for Treatment

In a second scenario, the case of an oncology patient who needed to travel from the region to another location for treatment was examined. The application identified relevant categories of socioeconomic support and benefits and presented possible next steps to the user.

The test allowed participants to assess:

  • the correct identification of the request,
  • the connection between different rights and benefits,
  • the completeness of the sources,
  • and the possibility of referral to the appropriate services.

At the same time, cases were also examined in which:

  • the question was unclear or incomplete,
  • the user did not know which right or benefit to look for,
  • clarifying questions were required,
  • medical or personalised legal advice was requested,
  • or immediate human intervention was necessary.

A Continuous Cycle of Scientific Feedback

The meeting concluded with a discussion of the testing results, a review of the technical logs and the presentation of key usage statistics for the application.

The participants’ observations are not treated as isolated comments, but as structured scientific feedback for improvement. In this way, a closed cycle of learning and feedback is created, in which technology, scientific knowledge and the experience of professionals interact continuously.

The continuous involvement of experts and the integration of structured feedback are considered critical for strengthening transparency, reliability and trust in Artificial Intelligence systems used in sensitive fields.

The Interdisciplinary Project Team

The development, scientific documentation and regulatory compliance of “Myrto” are supported by an interdisciplinary team from the fields of health services administration, information technology, personal data protection, language technology and software development. The workshop was attended by:

Evangeli Bista, Co-founder of Kapa3 and Head of Strategic Partnerships; Aristea Archontidou, Industrial Informatics Engineer with postgraduate specialisation in Health Policy and Health Services Planning; Anastasia Vlachopoulou, lawyer and member of the Thessaloniki Bar Association, specialised in personal data protection; Dimitris Papadakis, Co-founder and Sales Manager at SimasiaAI and Project Manager of the “Myrto” project; and Giannis Barous, Co-founder and CTO of SimasiaAI, PhD candidate in Computer Science based in San Francisco, who has undertaken the technical component of the project: how the system identifies the right information, how it connects it with reliable sources and how it provides answers that are evidence-based, useful and safe.

About Kapa3

The Cancer Patient Guidance Centre – Kapa3 is a social support, information and navigation organisation for oncology patients, survivors, caregivers and their families. Its aim is to contribute to equal access to oncology care, social protection and the rights associated with the cancer experience.

Every day, Kapa3 supports people who face not only the disease itself, but also a range of practical, administrative, social and psychosocial challenges. Through personalised social guidance, the organisation helps patients and caregivers learn about their rights, understand available benefits and services, navigate administrative procedures and connect with appropriate support structures.

The main pillars of Kapa3’s work include information on social and insurance rights, support in accessing health and social care services, guidance on benefits and procedures, empowerment of patients and caregivers, and connection with professionals, organisations and communities.

As part of its digital strategy, Kapa3 develops digital empowerment and social navigation tools, such as “Myrto”, the Digital Health and Social Rights Navigator. “Myrto” is designed to transform complex legal, administrative and social information into clear and evidence-based guidance for oncology patients, caregivers and citizens, always with human oversight, transparency and respect for the limits of technology.

Kapa3’s philosophy is based on the principle that care is not limited to medical treatment. It includes access to information, social protection, psychosocial support, dignity, empowerment and the ability of every person to know and claim their rights.

Through collaborations with health and social care professionals, academic and research institutions, civil society organisations, public structures, volunteers and communities, Kapa3 seeks to build bridges between the patient, information, services and real access.

Ηλικία, φύλο και ανοσοποιητικό σύστημα τα στοιχεία που αυξάνουν τον κίνδυνο θανάτου από covid19

Cancer Immunotherapy: A Revolution That Continues to Transform Cancer Care

Over the past fifteen years, cancer immunotherapy has transformed the landscape of oncology, offering new hope and treatment possibilities to patients around the world. What began as a promising scientific concept has evolved into one of the most important pillars of modern cancer treatment.

According to the Cancer Immunotherapy Insights & Impact Report 2026 published by the Cancer Research Institute, a total of 156 immunotherapy approvals were granted by the U.S. Food and Drug Administration (FDA) between 2011 and 2025, reflecting the remarkable growth and impact of this field. Many of these therapies are based on immune checkpoint inhibitors, which help the immune system recognize and attack cancer cells more effectively.

Unlike traditional treatments such as chemotherapy and radiation therapy, immunotherapy works by empowering the body’s own immune system to fight cancer. By enhancing natural immune responses, these therapies can help the body identify and destroy cancer cells that might otherwise evade detection. For many patients, immunotherapy has led to longer survival, improved disease control, and a better quality of life.

The year 2025 marked another milestone in the advancement of cancer immunotherapy, with thirteen new FDA approvals. Notably, patients with anal cancer gained access to their first approved immunotherapy option, highlighting the expanding reach of these innovative treatments. New methods of administration, including subcutaneous therapies, are also making treatment more convenient and accessible for patients.

Research in cancer immunotherapy continues to progress at an extraordinary pace. Scientists are developing new strategies to overcome the mechanisms that allow cancer to hide from the immune system, while exploring novel therapeutic targets, combination treatments, and personalized approaches to care. These advances aim to increase the number of patients who can benefit from immunotherapy and improve outcomes across a wider range of cancers.

While challenges remain and not all patients respond equally to treatment, immunotherapy represents one of the most significant breakthroughs in the history of cancer care. Ongoing scientific innovation continues to bring hope that more effective, personalized, and accessible treatments will become available in the years ahead.

At KAPA3, we recognize the importance of raising awareness about advances in cancer treatment and supporting informed decision-making. Knowledge empowers patients, families, caregivers, and healthcare professionals, helping them navigate the cancer journey with greater confidence and hope.

Source: https://www.cancerresearch.org/cancer-immunotherapy-report-2026


Kapa3 Cancer Patient Support Center and the USTEP Institute announce the launch of their strategic partnership

The Kapa3 Cancer Patient Support Center and the USTEP Institute announce the launch of their strategic partnership, aimed at providing meaningful support to cancer patients and promoting equal opportunities in scientific, social, and educational levels.

The partnership was formalized through the signing of a Memorandum of Understanding, which was signed in Athens on May 26, 2026, by Evangelia Bista, Co-founder and Head of Development and Operations at Kapa3, and Vasileios Stavrou, Co-founder and Scientific Director of the USTEP Institute.

As part of the collaboration, the two organizations will develop joint initiatives that include:

Organizing workshops and conferences focused on patient education, improving the quality of care, and strengthening the relationship of trust between patients and healthcare professionals.

The implementation of information and awareness campaigns on prevention, symptom management, and combating myths and social stigma surrounding cancer.

Collaboration on national and European programs aimed at developing innovative initiatives and actions with a social impact.

Conducting joint research and disseminating the results at the national and European levels.

This partnership reaffirms the two organizations’ commitment to actively contribute to the creation of a more supportive and inclusive environment for people living with cancer, by enhancing access to knowledge, information, and social empowerment.

The Memorandum of Cooperation is valid for one year, with the option to renew upon mutual written agreement by both parties.


MELODIC: Advancing Mental Health Support for Young Adults with Cancer

The MELODIC project, a European programme focused on the mental health of young adults with lived experience of cancer, launched in September 2024 with the aim of strengthening the mental wellbeing of people aged 18–35, as well as their families. Through collaboration among six European countries, MELODIC combines research, educational activities, and the development of future interventions, promoting a more supportive and personalised approach to care.

MELODIC has already delivered significant outcomes, including outputs related to project management, needs assessment, interview-based research, and the training of healthcare professionals, while preparing upcoming intervention actions and communication and policy strategies.

KEY DELIVERABLES – WHAT HAS BEEN COMPLETED SO FAR

WP1 – Project Management & Quality Assurance

Deliverable 1.1 – Project Implementation Manual:
A management and quality monitoring guide defining implementation requirements, organisational structures, and partner roles.

Deliverable 1.2 – Quality Report:
A quality assurance report outlining procedures to ensure clarity, consistency, and timely delivery of project outputs.

WP2 – Needs Assessment

Deliverable 2.1 – Data Management Plan:
Assessment of the mental health and educational needs of young adults and healthcare professionals, in full compliance with data protection requirements.

Deliverable 2.3 – Interview Study Report:
A comprehensive interview-based study involving young adults, family members, and healthcare professionals across six countries, conducted with ethical approval and presenting key findings.

WP3 – Co-design Guide & Training

Deliverable 3.1 – MELODIC Curriculum:
A training programme for healthcare professionals at EQF level 7, focusing on the identification and support of the psychosocial and mental health needs of young adults with cancer. The curriculum includes learning objectives, training materials, assessment methods, and certification.

WHAT’S NEXT – UPCOMING DELIVERABLES AND ACTIONS

WP4 – Intervention Study

Deliverable D4.1 – Ethical Review:
Ethical approval for the intervention study aiming to improve the mental health and wellbeing of young adults with cancer and their families. The intervention will combine physical activity in natural environments with psychoeducation and informational support.

WP5 – Communication & Policy

Deliverable 5.1 – Communication Strategy:
A communication strategy outlining channels, target audiences, and publication plans for the internal and external dissemination of project results.

Deliverable 5.2 – Policy Outreach Strategy:
A policy engagement strategy at European and national level, including policy and stakeholder mapping and three intervention pillars (European, National, and Project-specific). The aim is to integrate MELODIC training into curricula and to enhance the project’s visibility at European level.

OUR PARTICIPATION IN MELODIC

As part of our active involvement, we have contributed to the production of key deliverables, particularly in data collection through interviews and in the development of the training curriculum for healthcare professionals. Our engagement ensures that the voices of young adults with lived experience of cancer and their families are taken into account at every stage of the project.

For more information and full access to MELODIC deliverables, please visit the project’s official website here.

Text/adaptation: Ifiyenia Anastasiou for Kapa3
